Hearing and Thinking: The Connection That Surprises Almost Everyone
Quick Answer: Research consistently links untreated hearing loss with faster cognitive decline, and hearing loss is identified in major reviews as one of the largest potentially modifiable risk factors for dementia. The leading explanations are increased cognitive load during listening, reduced social engagement, and changes in brain structure from reduced auditory input. Evidence on hearing aids is promising but not conclusive, with the clearest benefit shown in people at higher baseline risk.
Most people file hearing under quality of life rather than under brain health. The research over the past decade has moved it firmly into the second category, and the size of the association surprises people who work in the field, let alone outside it.


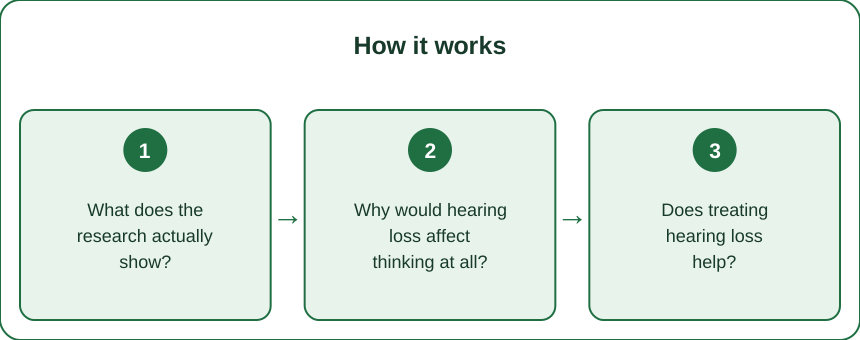
What does the research actually show?
The association is consistent across many studies, and it is larger than most single risk factors people worry about.
The headline finding: the Lancet Commission on dementia prevention has repeatedly identified hearing loss as one of the largest potentially modifiable risk factors across the life course, with particular weight in midlife. In their modelling, addressing hearing loss accounts for a meaningful share of the theoretically preventable proportion of dementia cases - a larger share than most other single factors on the list.
What the longitudinal studies show: people with hearing loss show faster rates of cognitive decline over follow-up periods of several years compared with people with normal hearing, and the effect appears to scale with severity. Mild, moderate, and severe hearing loss are associated with progressively higher risk in several large cohorts.
An important caution about what this means. These are observational findings, and association is not causation. Several alternative explanations have to be taken seriously:
- Reverse causation - early neurodegeneration could affect central auditory processing before it affects memory, meaning the hearing loss is an early symptom rather than a cause
- Common cause - vascular disease, diabetes, and inflammation damage both the cochlea and the brain, so both could be downstream of the same process
- Measurement artefact - cognitive tests are frequently administered verbally, and someone who cannot hear the instructions properly will score worse without having worse cognition. This is a genuine and underappreciated confound in some older studies.
Where the evidence is strongest: the association itself, which has been replicated many times across different populations and study designs. Where it is weakest: the causal claim, and specifically whether treating hearing loss changes cognitive trajectory - which is the question everyone actually wants answered.
The honest summary: hearing loss is a strong, consistent marker of elevated risk. Whether it is a cause that can be intervened on is a live research question with encouraging but incomplete answers.
Why would hearing loss affect thinking at all?
Three main mechanisms are proposed, and they are not mutually exclusive - most researchers think all three contribute.
Mechanism 1: Cognitive load and listening effort.
When the signal reaching the brain is degraded, the brain compensates by working harder to reconstruct it - filling in missing sounds from context, predicting words, using visual cues. This uses working memory and attention resources that would otherwise be available for understanding, remembering, and thinking about what is being said.
This is measurable. Studies using pupillometry and dual-task paradigms show that people with hearing loss expend more cognitive effort to achieve the same level of speech comprehension. The practical consequence is familiar to anyone with hearing loss: you follow the conversation but cannot remember it afterwards, because the resources needed to encode the memory were spent on hearing the words.
Over years, the argument goes, this represents a sustained diversion of cognitive resources - and it produces the exhaustion many people with hearing loss report after social events, which is genuine fatigue rather than a mood.
Mechanism 2: Social withdrawal.
Struggling to follow conversation in restaurants, groups, and family gatherings makes those situations tiring and sometimes humiliating. The common response is to attend less, and social isolation and loneliness are themselves well-established risk factors for cognitive decline.
This pathway is indirect and may be among the most important. Social engagement provides cognitive stimulation, emotional regulation, physical activity, and a reason to leave the house - and its withdrawal removes all of them simultaneously.
Mechanism 3: Structural brain change.
Imaging studies have found accelerated atrophy in the auditory cortex and in temporal lobe regions in people with hearing loss. The auditory cortex sits close to regions involved in memory, and reduced input appears to be associated with structural change - broadly the use-it-or-lose-it principle applied to a sensory pathway.
Whether this atrophy causes cognitive problems or simply reflects reduced input is not settled, but it provides a plausible biological route alongside the behavioural ones.
Does treating hearing loss help?
This is the question that matters, and the answer is genuinely mixed - promising rather than proven.
The most significant trial to date is ACHIEVE, a large randomised controlled trial published in 2023 that compared hearing intervention against a health education control in older adults over three years.
The headline result: across the whole study population, hearing intervention did not significantly slow cognitive decline compared to control.
The finding that drew attention: in the pre-specified subgroup at higher risk of cognitive decline - older participants with more risk factors, drawn from an existing cardiovascular study cohort - hearing intervention was associated with roughly a 48 percent reduction in the rate of cognitive decline over three years.
How to interpret this honestly:
- The overall null result matters and should not be skipped over
- The subgroup finding is striking and biologically plausible, and it was pre-specified rather than found by searching
- The healthy volunteer group declined very little overall, which makes a treatment effect hard to detect in a three-year window
- Subgroup findings require replication before being treated as established
What other evidence suggests: several observational studies have found that hearing aid users show slower cognitive decline than non-users with similar hearing loss, though people who choose and can afford hearing aids differ systematically from those who do not, which limits what can be concluded.
The reasonable position: hearing aids have clear, immediate, well-established benefits for communication, social participation, mood, and safety. Those benefits alone justify treatment. The possibility that they also protect cognition in higher-risk individuals is a genuine additional reason, held with appropriate uncertainty rather than as a promise.

What Nobody Tells You About Hearing and the Brain
The average delay between noticing hearing loss and doing something about it is around seven to ten years. That is a long time to spend under increased cognitive load and gradually reduced social contact, and it is the single most actionable fact in this whole area.
Hearing loss is under-treated to a striking degree. Estimates vary, but a large majority of adults who would benefit from hearing aids do not use them. Cost, access, stigma, and the slow onset all contribute - hearing loss develops so gradually that people adapt without noticing, and it is often a family member who identifies it first.
The exhaustion is real and is not laziness. People with untreated hearing loss frequently report being drained after social events, work meetings, or family gatherings. This maps directly onto the listening effort research. Naming it as cognitive load rather than as an attitude problem changes how it gets treated by everyone involved.
Your brain has to relearn hearing after aids are fitted. Sounds that have been absent for years return, and initially everything seems loud and artificial - rustling paper, footsteps, the fridge. This adaptation typically takes weeks to months, and it is the most common reason people abandon hearing aids in a drawer. Knowing to expect it substantially improves the odds of persisting.
Over-the-counter hearing aids changed access considerably. In the US, regulatory change in 2022 allowed direct sale of hearing aids for perceived mild to moderate hearing loss without a prescription, dropping prices dramatically. Quality varies, and a proper audiological assessment remains worthwhile - particularly to rule out treatable causes and one-sided loss, which needs medical evaluation.
Noise exposure is the modifiable part of the cause. Loud workplaces, headphones at high volume, and concerts all contribute cumulatively and irreversibly. A common rule of thumb is 60 percent volume for 60 minutes as a starting point for personal listening, and proper protection in loud environments. The hearing you protect at forty is the hearing you have at seventy.
Untreated hearing loss affects the people around you too. Family members raise their voices, repeat themselves, and often reduce how much they say. The withdrawal is frequently mutual, which accelerates the social isolation pathway from both directions.
What to do about it, practically
Get tested, and earlier than feels necessary.
- Baseline test in your fifties, or sooner with noise exposure, tinnitus, or family history
- Free or low-cost screening is widely available through audiologists, some pharmacies, and validated apps for initial screening
- Signs worth acting on: difficulty in restaurants and groups, turning the television up, asking for repetition, tinnitus, or a family member mentioning it
- Sudden hearing loss in one ear is a medical emergency - it needs same-day assessment, as treatment is time-sensitive
If you have hearing loss:
- Treat it rather than adapting to it. Adaptation is what costs the cognitive load.
- Expect an adjustment period of weeks to months and persist through it - support from an audiologist during this window matters
- Wear them consistently. Intermittent use gives the brain no chance to readapt.
- Ask about assistive options beyond aids - phone captioning, TV streaming, loop systems in public venues
Protect what you have:
- Hearing protection in loud environments - concerts, power tools, motorbikes, loud workplaces
- Moderate headphone volume, particularly with noise-cancelling headphones, which paradoxically enable safer listening by removing the need to drown out background noise
- Manage cardiovascular health. The cochlea depends on tiny blood vessels, and hypertension, diabetes, and smoking all damage them. This is also the common-cause pathway - what protects your hearing largely protects your brain.
Address the social pathway directly, since it may be the most important:
- Choose quieter venues for conversation rather than declining the invitation
- Sit with your back to noise and with a view of faces - lip reading contributes more than people realise
- Tell people you have hearing loss. It is the single most effective communication strategy and the one people most avoid.
The broader point: hearing is one item on a list of modifiable risk factors that includes physical activity, blood pressure, smoking, alcohol, social contact, education, air pollution, and head injury. It is unusual on that list in being both very common and very treatable, which is why it is worth a specific appointment rather than a general intention.
FAQ: Hearing and Cognitive Health, Answered
Does hearing loss cause dementia?
The association is strong and consistent; causation is not established. Hearing loss may be a cause, an early symptom, or a marker of shared vascular damage - possibly all three in different people. Treating it is worthwhile regardless.
Will hearing aids prevent dementia?
No one can currently say that. The ACHIEVE trial found no overall effect but a substantial benefit in a higher-risk subgroup. Hearing aids have well-established benefits for communication, mood, and social participation independent of any cognitive effect.
At what age should I get my hearing tested?
A baseline in your fifties is reasonable, sooner with noise exposure, tinnitus, or symptoms. Since the average person waits nearly a decade after noticing problems, earlier is nearly always better.
Are over-the-counter hearing aids any good?
For perceived mild to moderate loss, regulated OTC devices can be effective and are far cheaper. A proper audiological assessment is still worth having, especially for one-sided loss, sudden loss, or pain, all of which need medical evaluation.
Is tinnitus related to cognitive decline?
Tinnitus commonly accompanies hearing loss, and the underlying hearing loss is the relevant factor. Persistent tinnitus, particularly in one ear or of sudden onset, should be assessed by a doctor. This article is general information, not medical advice - speak to a healthcare professional about your own hearing and health.
TL;DR:
- Hearing loss is identified in major reviews as one of the largest modifiable risk factors for later cognitive decline
- The likely mechanisms are cognitive load from effortful listening, social withdrawal, and reduced auditory input to the brain
- The largest trial found no overall cognitive benefit from hearing aids, but a substantial benefit in a higher-risk subgroup
- People wait around seven to ten years before acting - that delay is the most actionable part
- Protect hearing with volume limits and ear protection, and treat cardiovascular health, which affects both ear and brain
If you have been turning the television up, asking people to repeat themselves in restaurants, or coming home from social events unusually drained, that is worth a hearing test this month. The communication benefit is certain and immediate. The possible cognitive benefit is a reason to stop waiting. This is general information, not medical advice.
Keep Reading
This article is for general informational purposes only and is not medical advice. Always consult a qualified health professional for guidance specific to you.
